Why this case matters
Retinitis pigmentosa (RP) is often recognized by difficulty seeing in dim light, progressive loss of side vision, and changes in the retina. Yet RP can sometimes be part of a broader condition affecting other parts of the body, including the nervous system. Recognizing those connections can be especially important for people whose eye disease is accompanied by symptoms that do not seem to fit a typical RP diagnosis.
A 2026 case report in Case Reports in Ophthalmology describes a 31-year-old woman with RP, a Coats-like retinal reaction, and two identified FLVCR1 variants. Her case draws attention to an important clinical message: when a person with RP also has unexplained neurologic symptoms, clinicians may need to revisit the genetic and neurologic picture together rather than treating each problem as unrelated.
RP with a Coats-like reaction
The patient had long-standing nyctalopia, or poor vision in low light, a hallmark symptom of RP. She also had a Coats-like reaction, a retinal complication in which abnormal blood vessels can leak fluid and fats into the retina. Although named for its resemblance to Coats disease, a Coats-like reaction can occur in association with inherited retinal disorders such as RP.
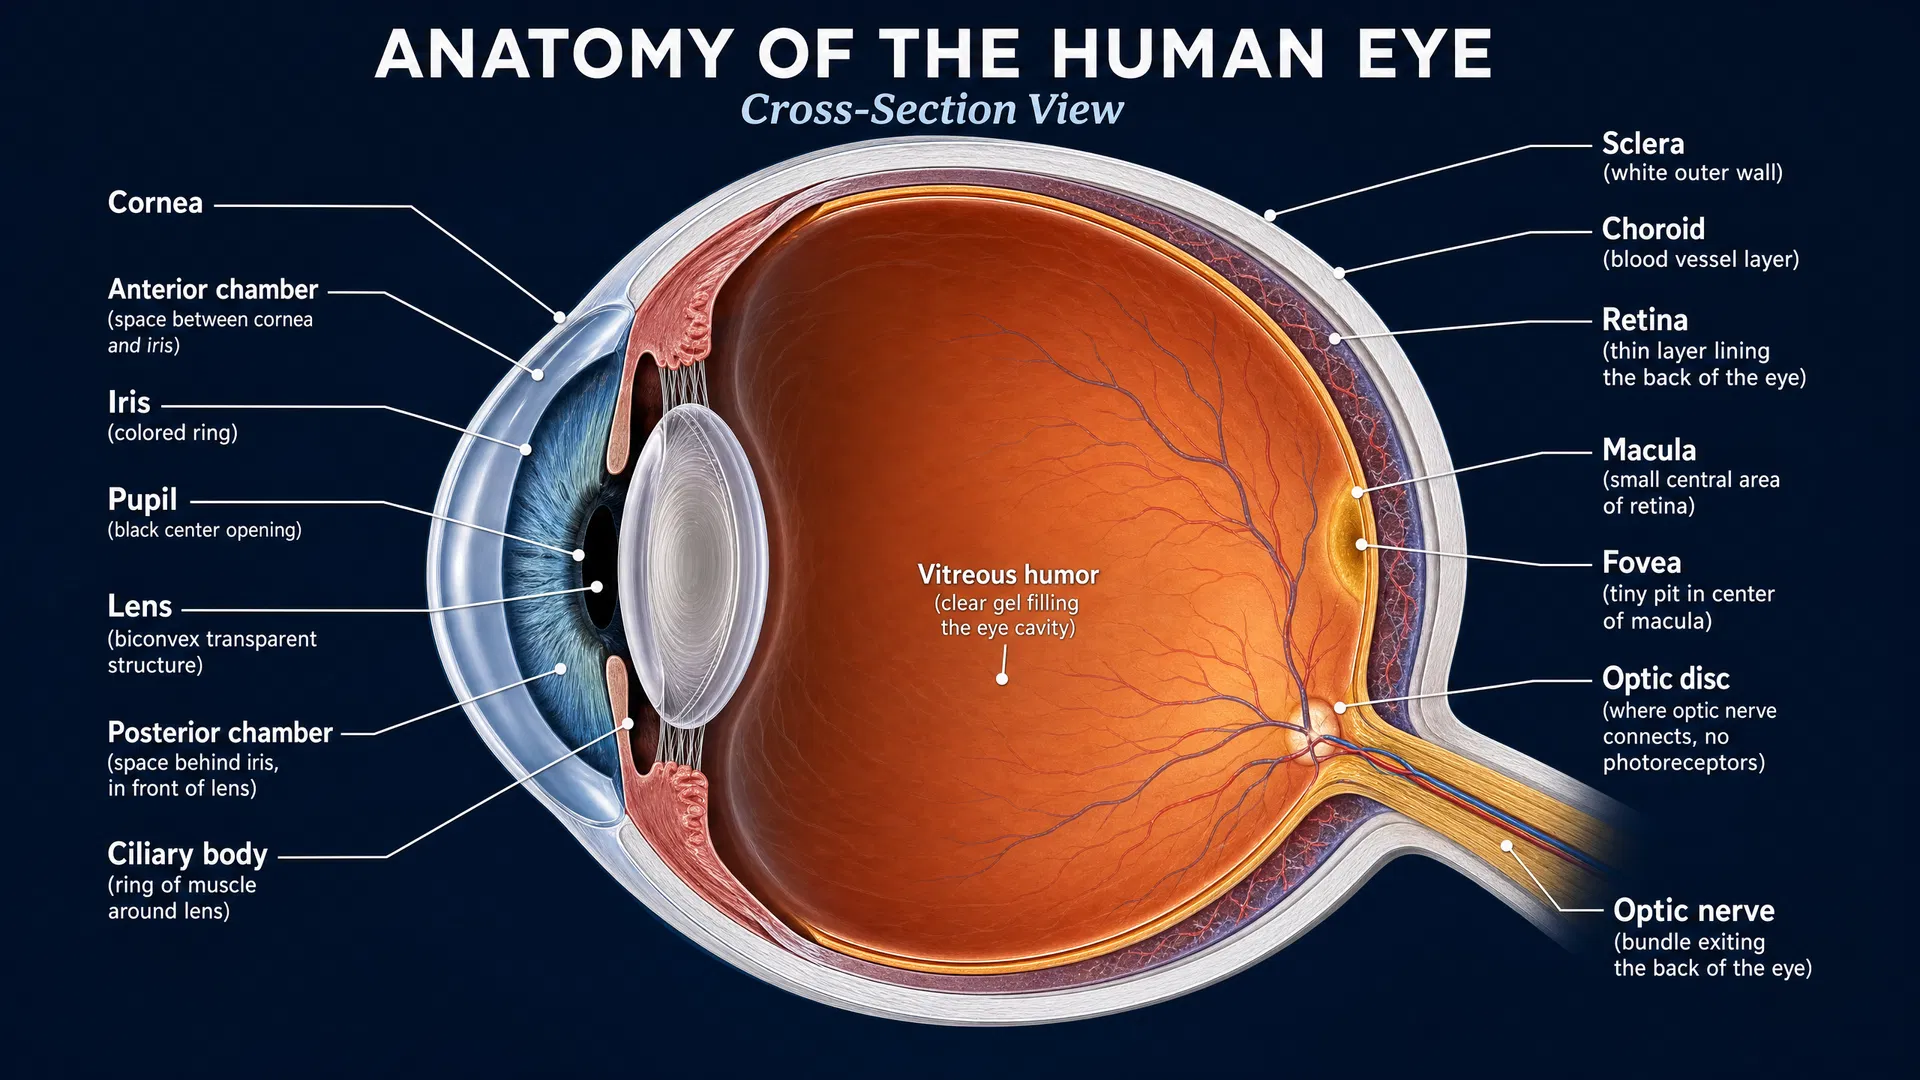
In this case, the leakage had serious implications for central vision. When the patient returned to the eye clinic in February 2025, she reported worsening central vision, pain in her right eye, and continuing leg instability. Optical coherence tomography (OCT), a noninvasive retinal imaging test, showed cystoid macular edema, attenuated retinal blood vessels, and a large amount of lipid exudation in the fovea of the right eye. The fovea is the small central region of the retina responsible for detailed, straight-ahead vision, so changes in this area can have a major impact on everyday tasks such as reading and recognizing faces.
A genetic finding alongside an overlooked neurologic history
Genetic testing identified two FLVCR1 changes: c.1092 + 5G>A and c.1058C>T, p.(Thr353Met). The report describes the patient as heterozygous for each variant. FLVCR1 is therefore a key focus of the case, which expands the clinical picture associated with FLVCR1 variants.
Crucially, the eye findings were not the patient’s only health concern. Over approximately six years, she had experienced migraine headaches, reduced strength in her extremities, seizure-like episodes, and urinary incontinence. Her leg weakness and spasms progressed to the point that weight bearing and walking became impaired. Despite prior genetic testing, these neurologic features had remained undiagnosed.
The report does not suggest that every person with RP and neurologic symptoms will have an FLVCR1 variant. Instead, it illustrates why apparently separate symptoms deserve to be considered together. A detailed history—including mobility changes, muscle spasms, episodes concerning for seizures, bladder symptoms, and headaches—may reveal a pattern that calls for coordinated retinal, genetic, and neurologic evaluation.
Treating the vision-threatening complication
The case also offers a practical treatment observation for Coats-like retinal leakage. The patient began anti-VEGF therapy in February 2025. Anti-VEGF medicines are used to reduce the effects of vascular endothelial growth factor, a signaling molecule involved in abnormal blood-vessel leakage.
One month after treatment began, follow-up OCT showed reduced lipid exudation. This response supports anti-VEGF therapy as a potentially useful approach for reducing lipid leakage in Coats-like retinopathy. For patients with RP, this is important because the inherited retinal degeneration itself and a potentially treatable vascular complication may coexist. Monitoring with retinal imaging can help identify changes such as macular edema or exudation that may be contributing to a recent decline in central vision.
This single case cannot establish how well anti-VEGF treatment works for all people with RP-related Coats-like reactions, nor does it show whether treatment changes the underlying retinal degeneration. It does, however, show that leakage in the macula may improve on imaging after therapy.
What this means for families and future care
For patients and families, the central lesson is that genetic results can be clinically meaningful beyond the eye. An RP diagnosis should not prevent clinicians from investigating progressive neurologic symptoms, and unexplained neurologic symptoms should not be dismissed as unrelated when an inherited retinal disorder is present.
For care teams, this report reinforces the value of combining genetic testing, retinal imaging, and ongoing clinical reassessment. A result obtained earlier in a patient’s journey may take on new importance when additional symptoms emerge or progress.
Looking ahead
Rare-disease case reports often provide the first clues that broaden understanding of how a gene-related condition can appear in real life. This report expands awareness of retinal and neurologic dysfunction in the setting of FLVCR1 variants and RP with a Coats-like reaction. Future studies involving more patients will be needed to clarify the full range of neurologic findings, the relationship between specific FLVCR1 variants and retinal disease, and the most effective strategies for managing vascular leakage.
For now, the case highlights a forward-looking principle in inherited retinal disease research and care: better outcomes may depend not only on identifying the retinal diagnosis, but also on recognizing the whole-person pattern that surrounds it.