Why this case matters
Fundus albipunctatus is a retinal condition recognized by numerous small, pale flecks across the back of the eye and by difficulty seeing in dim light or darkness. When clinicians see this pattern—especially alongside progressive night blindness—they may understandably consider an inherited retinal dystrophy. For patients and families, that possibility can bring urgent questions about genetic causes, prognosis, and whether treatment is available.
A 2026 BMJ Case Reports publication offers an important reminder: a fundus albipunctatus-like appearance does not always have an inherited retinal cause. In this report, a young man with night blindness, optic nerve disease, and retinal flecks was ultimately found to have severe vitamin A deficiency together with skull hyperostosis, an abnormal thickening of cranial bone that narrowed the optic canals. Crucially, the retinal findings improved after vitamin A supplementation.
The case highlights the value of looking beyond a first, seemingly obvious diagnosis. It also demonstrates why genetic test results must be interpreted alongside the full clinical picture.
A presentation that initially resembled retinal dystrophy
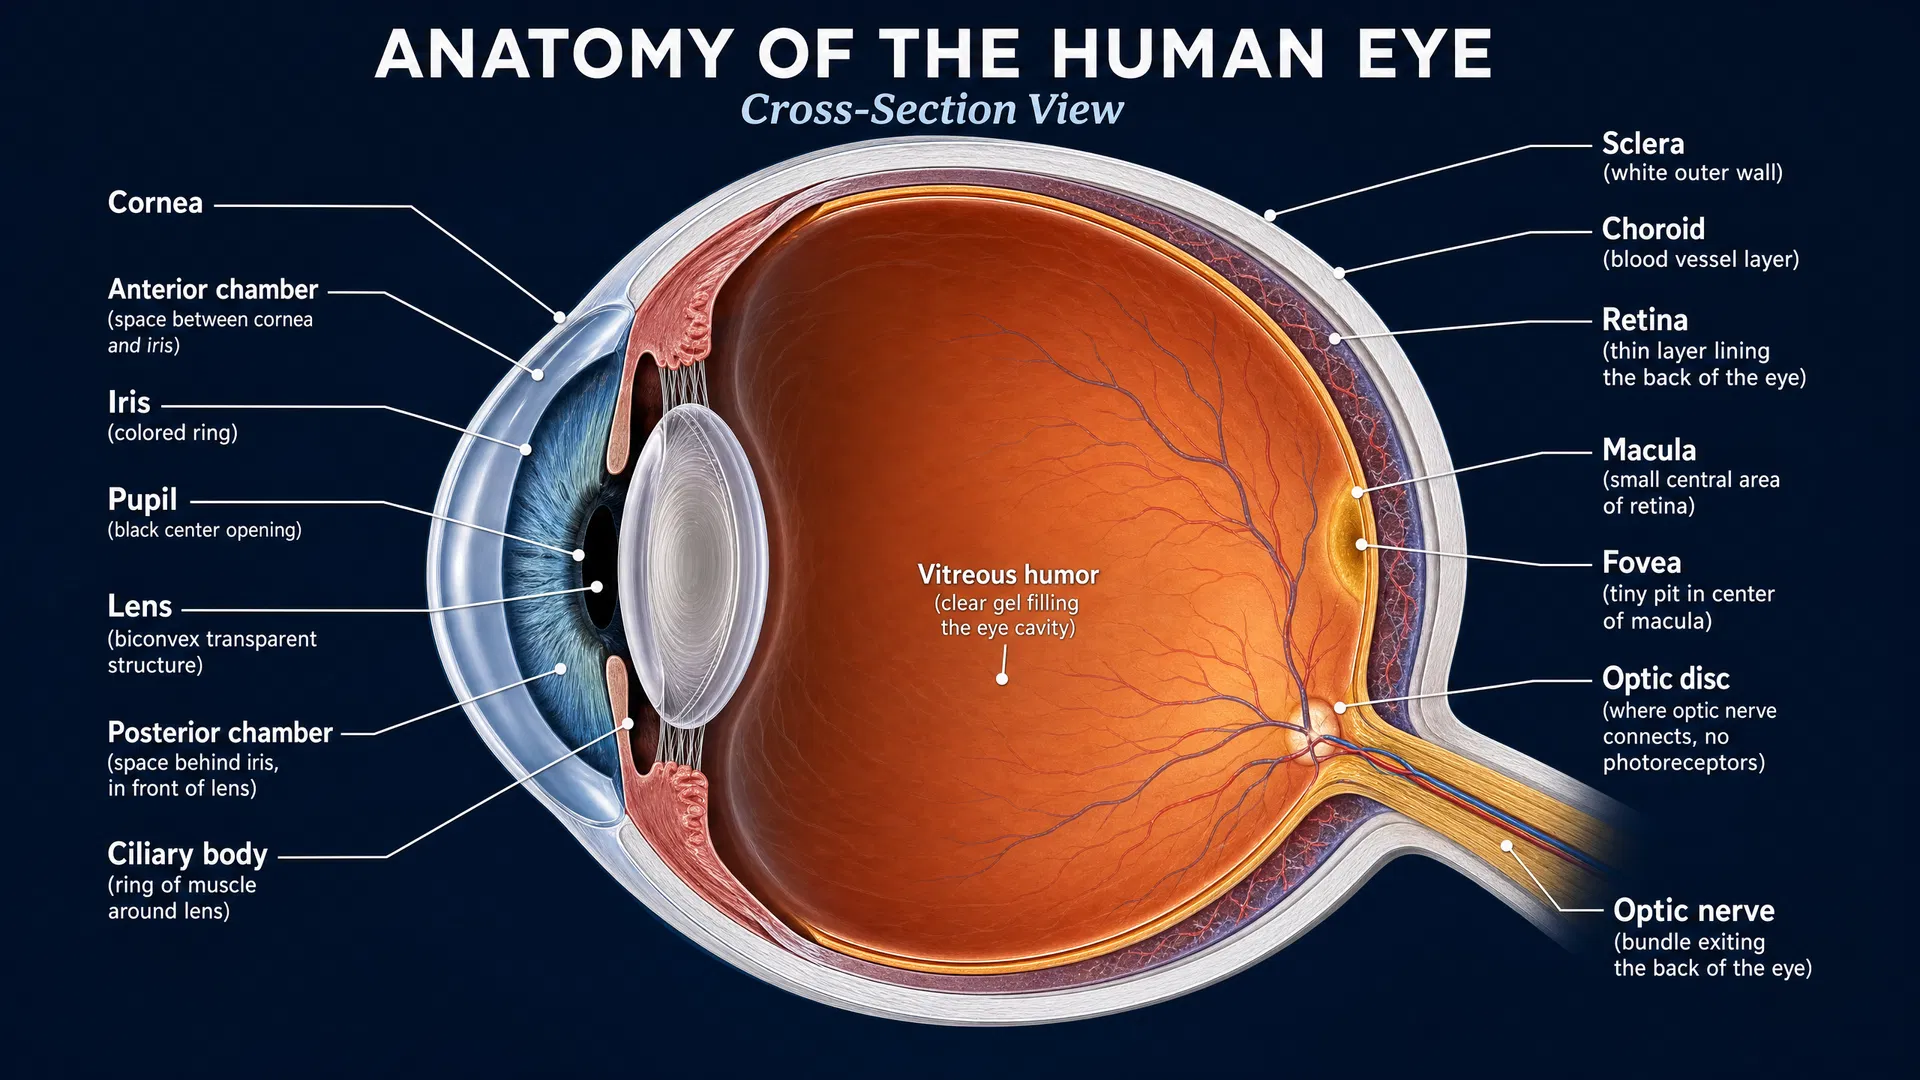
The patient developed progressive night blindness and had bilateral retinal flecks, meaning that the flecks were present in both eyes. These findings can resemble fundus albipunctatus and other inherited retinal disorders. However, he also had optic neuropathy, a problem affecting the optic nerve—the pathway that carries visual information from the eye to the brain.
Genetic testing identified one heterozygous pathogenic variant in USH2A, as well as several variants of uncertain significance. A heterozygous finding means that a variant was identified in one copy of a gene. A variant of uncertain significance is a genetic change for which available evidence does not establish whether it is harmful or benign.
Although these results were potentially relevant, they did not fully account for the patient’s overall pattern of disease. This was the turning point in the diagnostic process. Rather than assuming that the genetic findings explained the retinal changes, the clinical team continued investigating.
Vitamin A deficiency and optic canal narrowing
Further assessment revealed severe vitamin A deficiency. Vitamin A is closely linked to vision in low-light conditions, making deficiency a particularly important consideration when a person develops night blindness. In this patient, it was associated with retinal changes that mimicked an inherited retinal dystrophy.
The investigation also identified cranial hyperostosis, with narrowing of the optic canals. The optic canals are bony passages through which the optic nerves travel from the eyes toward the brain. Narrowing in this region can affect the optic nerves and offers a structural explanation for the optic neuropathy seen in this case.
Together, these findings showed that more than one process could be contributing to visual symptoms: vitamin A deficiency was relevant to the night blindness and flecked retinal appearance, while skull hyperostosis and optic canal narrowing were important clues in understanding the optic nerve involvement.
Improvement after supplementation: a key message
One of the most significant findings was that the retinal appearance improved following vitamin A supplementation. This response supports vitamin A deficiency as a reversible contributor to the retinal pathology.
For people evaluated for fundus albipunctatus or a similar flecked-retina presentation, the message is not that inherited disease is unimportant. Rather, it is that retinal imaging, symptoms, genetic testing, nutritional assessment, and evaluation of the optic nerves all need to be considered together. An inherited retinal diagnosis should fit the complete clinical picture—not only one examination finding or one genetic result.
This is especially important when the presentation includes features that are not fully explained by the suspected inherited condition. In this report, optic neuropathy and the later discovery of cranial bone abnormalities made collaboration beyond ophthalmology essential.
Implications for treatment and care
The case places treatable contributors at the center of the assessment process. Identifying severe vitamin A deficiency can create an opportunity for intervention, as demonstrated by the improvement in retinal findings after supplementation. It also reinforces that treatment planning may require attention to both retinal health and the optic nerve pathway.
The publication emphasizes a multidisciplinary model involving ophthalmology, neurology, medical genetics, and neurosurgery. Each specialty contributed a different piece of the diagnostic puzzle: retinal findings and night blindness; optic nerve involvement; careful interpretation of genetic results; and recognition of skull hyperostosis with optic canal narrowing.
For families, this approach underscores that genetic testing is a powerful tool, but it is not a stand-alone answer. A pathogenic variant or uncertain variant must be assessed in the context of symptoms, eye findings, and other medical investigations.
Looking ahead
This report expands the conversation around fundus albipunctatus-like retinal changes by showing how closely a reversible nutritional condition can resemble inherited retinal disease. As genetic testing becomes increasingly common, the ability to distinguish causative findings from incidental or incomplete genetic explanations will remain essential.
Future progress will depend on integrated care: precise retinal assessment, thoughtful genetic interpretation, and continued attention to systemic and structural causes of visual loss. For patients with night blindness and retinal flecks, this case offers a hopeful and practical lesson—careful investigation can uncover factors that may be addressed, even when the first impression points toward an inherited disorder.