Why this study matters
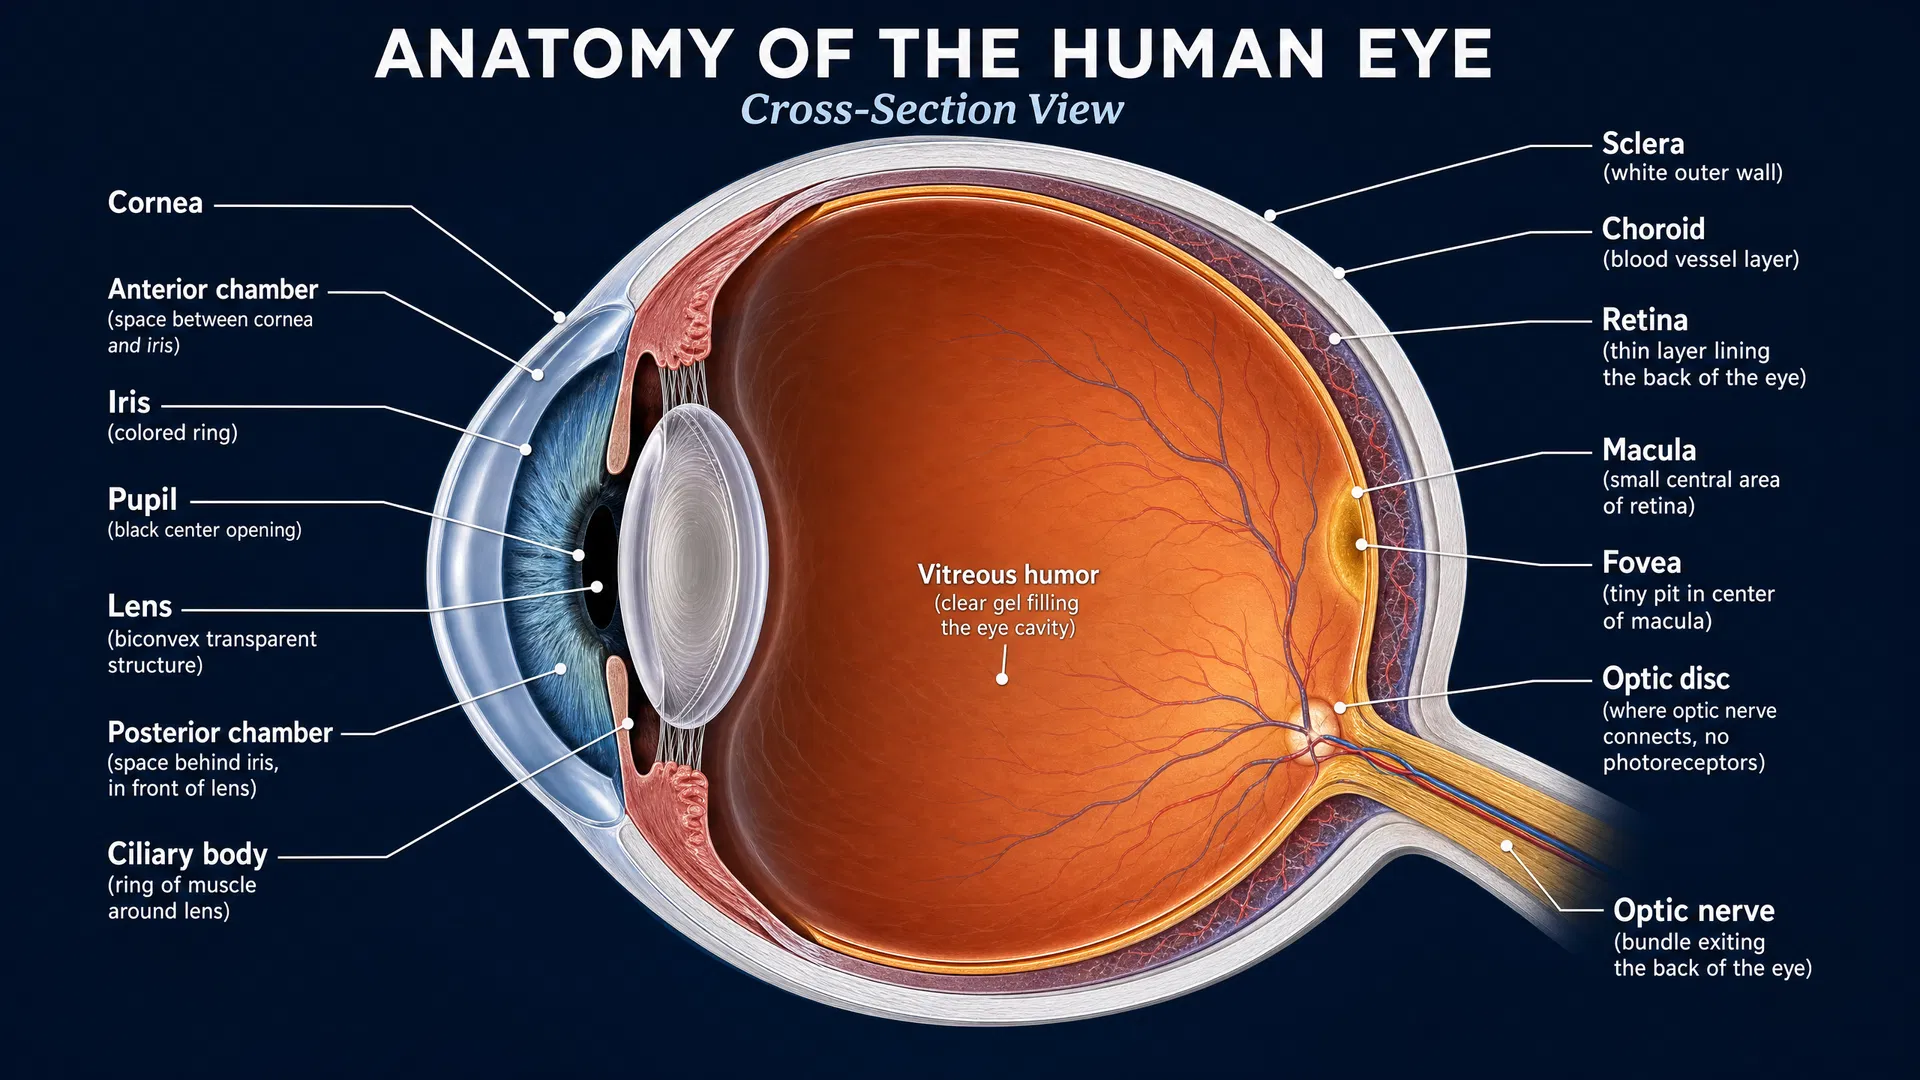
Stargardt disease is an inherited retinal disease that damages the macula, the central part of the retina needed for detailed tasks such as reading and recognizing faces. Researchers are pursuing several strategies to slow the processes that contribute to retinal damage. One approach focuses on vitamin A, or retinol, transport.
Retinol is essential for vision, but its movement through the body and into the eye must be tightly regulated. Retinol-binding protein 4 (RBP4) carries retinol in the bloodstream. In the eye, retinoid compounds are part of the visual cycle—the series of chemical steps that allows photoreceptor cells to respond to light. In Stargardt disease, disease-related changes in this system can contribute to the buildup of harmful vitamin A-derived byproducts in the retinal pigment epithelium, a support layer critical to photoreceptor health.
Tinlarebant is an investigational medicine designed to target RBP4. It has been reported to slow macular lesion growth in people with Stargardt disease, but the detailed biological basis for its action had not been publicly described. This 2026 study provides structural and biochemical evidence showing how tinlarebant engages RBP4 and lowers RBP4 levels in the circulation.
RBP4, retinol, and transthyretin: a transport partnership
RBP4 normally carries retinol in the blood. This retinol-loaded form of the protein is often called holo-RBP4. RBP4 also forms a complex with another blood protein, transthyretin (TTR). This partnership helps stabilize RBP4 in circulation.
The researchers examined whether tinlarebant could occupy RBP4’s retinol-binding pocket—the site where retinol normally binds—and what would happen to RBP4’s interaction with TTR. Their findings support a two-part mechanism: tinlarebant displaces retinol from RBP4, then prevents RBP4 from associating with TTR.
Key findings from the study
Tinlarebant strongly competes with retinol
Using fluorescence-based experiments, the investigators found that tinlarebant competitively displaced retinol from holo-RBP4. The reported IC50 was 8.75 ± 0.38 nanomolar, indicating that tinlarebant binds tightly and can compete effectively with retinol at very low concentrations.
Put simply, tinlarebant occupies the same functional pocket that RBP4 uses to carry retinol. This is important because blocking that pocket can reduce the amount of retinol transported by RBP4.
The drug-bound protein does not form its usual complex with TTR
The team used size-exclusion chromatography, a method that separates molecules based on their size and interactions, to study the RBP4–TTR partnership. RBP4 bound to tinlarebant failed to associate with TTR in these laboratory experiments.
This result helps explain why targeting RBP4 may lower circulating RBP4. Without its normal interaction with TTR, RBP4 may be less stable in plasma or handled differently by the body.
A crystal structure revealed how the disruption occurs
The crystal structure of the RBP4–tinlarebant complex provided a close-up view of the interaction. According to the authors, tinlarebant prevents RBP4 from binding TTR through both conformational and steric effects. In other words, the drug changes features of RBP4’s shape while also physically getting in the way of the protein-protein interaction.
The study also notes that tinlarebant incorporates multiple features of earlier RBP4 antagonists, including A1120, an early lead compound from which tinlarebant was derived. This structural information can help researchers understand which drug features are most important for strong RBP4 binding and TTR disruption.
Tinlarebant sharply reduced plasma RBP4 in mice
After single doses of tinlarebant, mice showed reductions in plasma RBP4 of up to 93%. This finding connects the laboratory observations to an effect in a living organism: interfering with the RBP4–TTR interaction was associated with substantially lower circulating RBP4.
What this could mean for Stargardt disease treatment research
The findings clarify the pharmacology behind an approach intended to reduce retinol delivery through the RBP4 transport system. For Stargardt disease, the therapeutic goal is not to eliminate vitamin A biology altogether. Rather, it is to modulate a pathway linked to the formation of damaging retinal byproducts.
This study does not establish clinical benefit on its own, nor does it answer every question about long-term treatment. However, it offers a strong mechanistic foundation for interpreting clinical research on tinlarebant. It shows that the compound is not simply associated with lower RBP4 levels: it binds in RBP4’s retinol pocket, blocks its interaction with TTR, and produces a major reduction in circulating RBP4 in mice.
The work may also inform development of future RBP4 antagonists. Detailed structural knowledge can support efforts to design compounds with effective target engagement and desirable drug properties.
Looking ahead
Stargardt disease research increasingly combines insights from genetics, retinal biology, imaging, and drug development. Tinlarebant represents a non-gene-specific strategy: rather than correcting the underlying inherited change directly, it aims to modify a biochemical pathway relevant to disease processes.
This publication adds an important piece to that research landscape by explaining how tinlarebant acts at the molecular level. Continued clinical research will be needed to determine how changes in RBP4 and retinol transport translate into meaningful long-term outcomes for people living with Stargardt disease. Together, mechanistic studies like this one and patient-centered clinical studies can help guide the next generation of treatments.