CRB1 — Crumbs Family Member 1, Polarity Complex Component
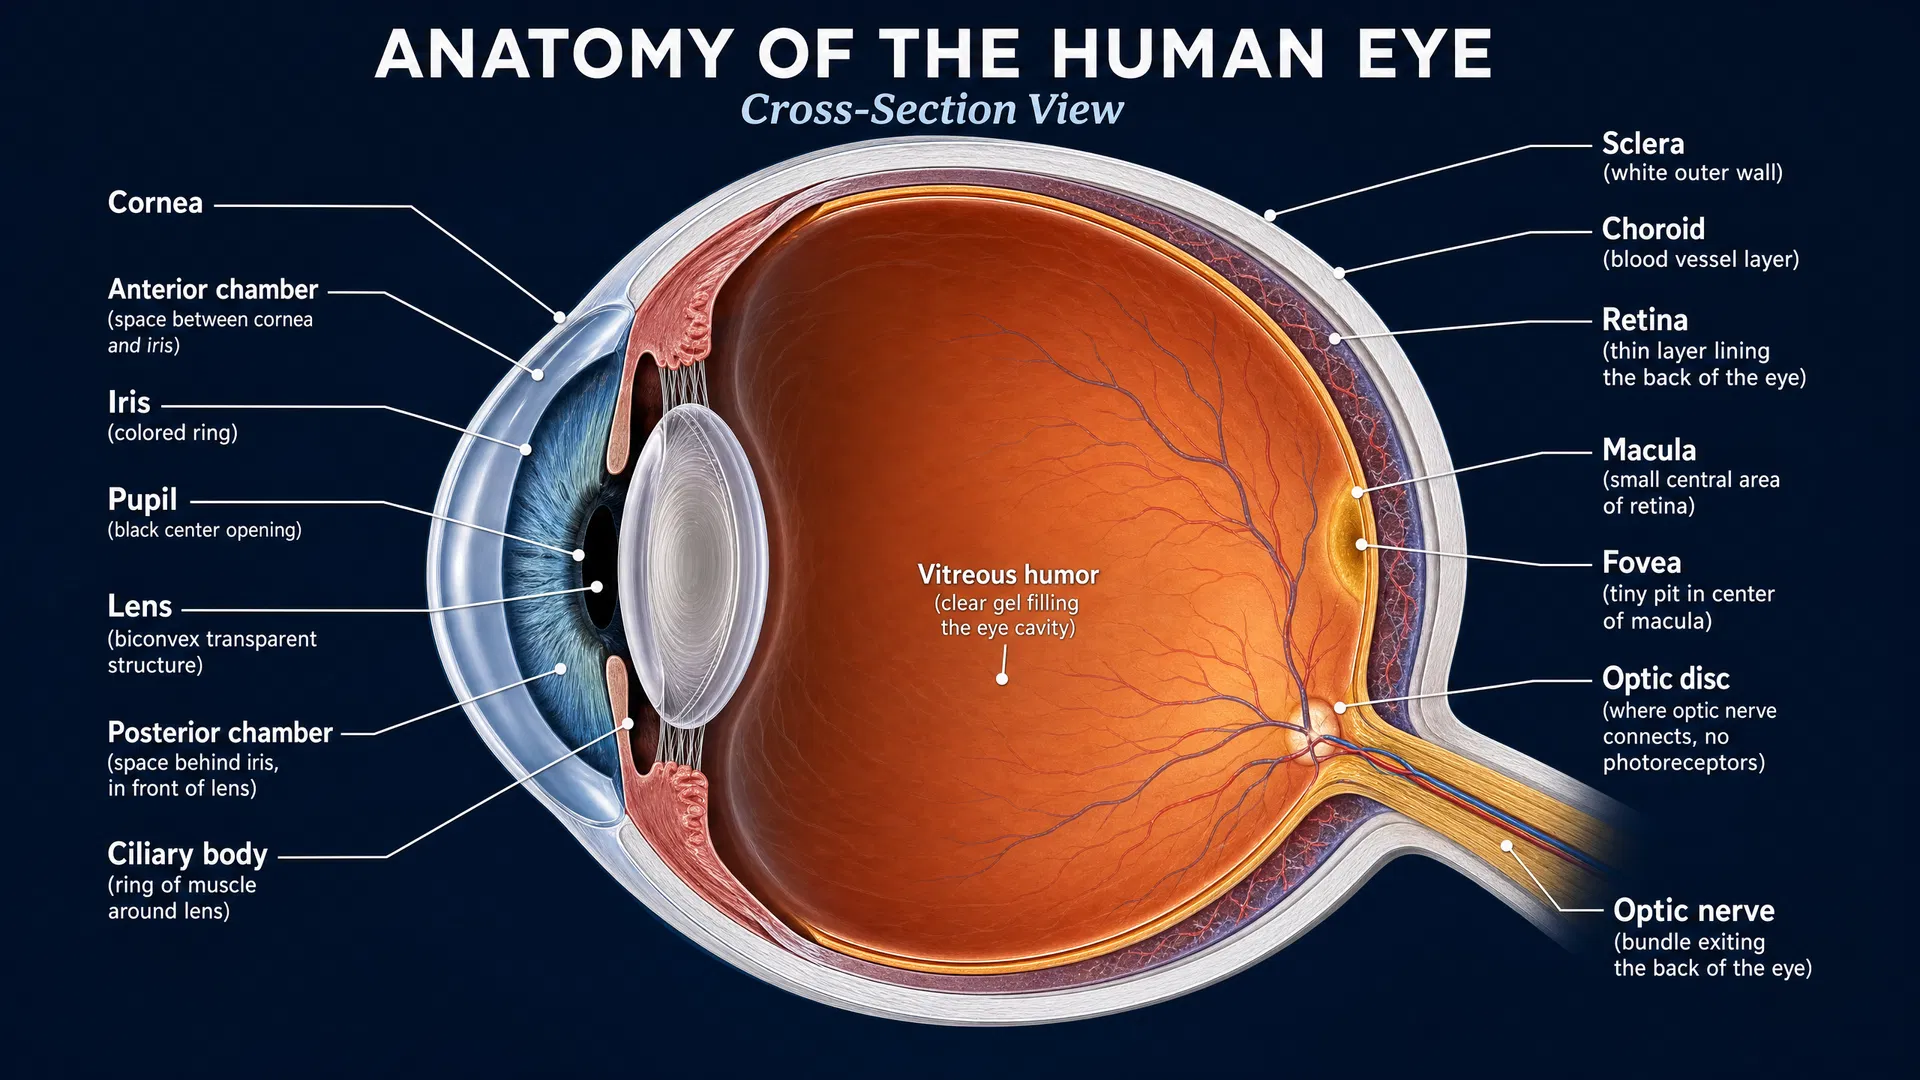
The CRB1 gene provides essential instructions for making a protein that is crucial for normal vision. This protein is primarily found in the retina, the light-sensitive tissue at the back of the eye. The CRB1 protein acts like a structural scaffold or glue; it helps to organize the light-sensing cells (photoreceptors) and supporting cells in the retina, ensuring they are properly aligned and connected. This organization is vital for the retina to develop correctly and function properly throughout life. When there are harmful changes (mutations) in the CRB1 gene, the protein may be missing, too short, or unable to function correctly. Without this crucial support, the retina does not develop its normal layered structure and becomes unusually thick and disorganized. Over time, the light-sensing cells begin to break down and die. This leads to a group of inherited eye disorders known as CRB1-associated retinal dystrophies, which include conditions like Leber congenital amaurosis (LCA) and retinitis pigmentosa (RP). Patients may experience severe vision loss starting at birth or in early childhood, night blindness, and a progressive loss of peripheral (side) vision. These conditions are inherited in an autosomal recessive pattern. This means that a person must inherit two mutated copies of the CRB1 gene—one from each parent—to develop the disease. The parents, who each carry one mutated copy, are typically unaffected and have normal vision. For families with an affected child, genetic testing and counseling are important to understand the diagnosis, the progression of the disease, and the chances of the condition appearing in future children.
Gene description: Encodes a transmembrane protein crucial for maintaining photoreceptor polarity and retinal organization.
Patient and family guide: The CRB1 gene provides essential instructions for making a protein that is crucial for normal vision. This protein is primarily found in the retina, the light-sensitive tissue at the back of the eye. The CRB1 protein acts like a structural scaffold or glue; it helps to organize the light-sensing cells (photoreceptors) and supporting cells in the retina, ensuring they are properly aligned and connected. This organization is vital for the retina to develop correctly and function properly throughout life. When there are harmful changes (mutations) in the CRB1 gene, the protein may be missing, too short, or unable to function correctly. Without this crucial support, the retina does not develop its normal layered structure and becomes unusually thick and disorganized. Over time, the light-sensing cells begin to break down and die. This leads to a group of inherited eye disorders known as CRB1-associated retinal dystrophies, which include conditions like Leber congenital amaurosis (LCA) and retinitis pigmentosa (RP). Patients may experience severe vision loss starting at birth or in early childhood, night blindness, and a progressive loss of peripheral (side) vision. These conditions are inherited in an autosomal recessive pattern. This means that a person must inherit two mutated copies of the CRB1 gene—one from each parent—to develop the disease. The parents, who each carry one mutated copy, are typically unaffected and have normal vision. For families with an affected child, genetic testing and counseling are important to understand the diagnosis, the progression of the disease, and the chances of the condition appearing in future children.
Gene function: CRB1 plays a vital role in maintaining the apical-basal polarity of photoreceptor cells and the structural integrity of the outer limiting membrane in the retina. It is involved in cell-cell adhesion and signaling pathways, which are critical for photoreceptor survival, differentiation, and the overall organization of the retinal layers, impacting visual function.
Protein structure: The CRB1 gene encodes a large, single-pass Type I transmembrane protein, typically consisting of 1376 or 1406 amino acids depending on the splice variant. The protein is characterized by a massive extracellular domain, a single transmembrane segment, and a very short intracellular cytoplasmic tail (about 37 amino acids). The extracellular region contains 19 epidermal growth factor (EGF)-like domains and 3 laminin A globular (AG)-like domains, which are crucial for mediating cell-cell interactions and homophilic or heterophilic binding with other proteins in the extracellular space. The short intracellular domain is highly conserved and contains specific binding motifs, including a FERM-binding domain and a PDZ-binding motif at the extreme C-terminus. These motifs are essential for assembling the Crumbs polarity complex by recruiting intracellular scaffolding proteins like PALS1 and PATJ. This assembly links the CRB1 protein to the actin cytoskeleton and other signaling networks, allowing it to function as a critical regulator of cell polarity and adhesion in the retina.
Molecular function: The CRB1 gene encodes Crumbs homolog 1, a transmembrane protein that is a core component of the Crumbs cell polarity complex. This complex is essential for establishing and maintaining apicobasal cell polarity and the formation of adherens junctions in epithelial tissues. In the retina, CRB1 localizes to the subapical region, just apical to the adherens junctions that form the outer limiting membrane (OLM), which connects photoreceptors and Müller glial cells. At the molecular level, the short intracellular domain of CRB1 interacts with scaffolding proteins such as PALS1 (protein associated with Lin seven 1) and PATJ (PALS1-associated tight junction protein). These interactions anchor the Crumbs complex to the cytoskeleton and coordinate with other polarity complexes, such as the Par and Scribble complexes. This network is crucial for photoreceptor morphogenesis, proper retinal lamination during development, and the long-term structural integrity of the retina. Loss of CRB1 function disrupts these critical cell-cell adhesions and polarity cues. This disruption leads to a failure in maintaining the OLM, resulting in the disorganization of the photoreceptor layer, abnormal retinal thickening, and eventual photoreceptor degeneration. The protein also appears to play a role in regulating cell proliferation and apoptosis during retinal development, further explaining the severe developmental defects seen in CRB1-associated diseases.
Expression pattern: The CRB1 gene is predominantly expressed in the retina and the brain. Within the retina, the CRB1 protein is localized to the subapical region adjacent to the adherens junctions at the outer limiting membrane (OLM). It is expressed in both photoreceptor cells (rods and cones) and Müller glial cells. The expression of CRB1 is critical during retinal development for the proper morphogenesis and lamination of the retina. It continues to be expressed in the mature retina, where it plays an essential role in maintaining cell polarity, adhesion, and the structural integrity of the photoreceptor layer. Alternative splicing of the CRB1 gene yields different transcripts, with the major isoforms encoding proteins of 1376 and 1406 amino acids, which may have distinct functional roles or subcellular localizations.
Mutation spectrum: The mutation spectrum of the CRB1 gene is highly diverse, with over 300 pathogenic variants identified to date. These include missense, nonsense, frameshift, splice-site mutations, and small insertions or deletions. Missense mutations are the most common, often affecting the highly conserved EGF-like or laminin A globular-like domains in the extracellular portion of the protein, disrupting proper folding or protein-protein interactions. While mutations are distributed throughout the gene, certain variants are more prevalent in specific populations. For example, the missense variant c.2843G>A (p.Cys948Tyr) is one of the most frequently reported pathogenic alleles. Null mutations, which result in a truncated or absent protein, are generally associated with more severe phenotypes like LCA, whereas some missense mutations may allow for partial protein function and result in milder, later-onset diseases.
Pathogenic variants: 1. p.Cys948Tyr (c.2843G>A) - One of the most common missense variants, frequently associated with severe phenotypes like LCA and EOSRD. 2. p.Ile167_Gly169del (c.498_506del) - An in-frame deletion that is specifically associated with the milder macular dystrophy (MD) phenotype. 3. p.Arg764Cys (c.2290C>T) - A well-characterized missense mutation that disrupts a critical cysteine residue, leading to protein misfolding and associated with LCA/RP. 4. p.Pro836Thr (c.2506C>A) - A missense variant that has been linked to a mild, stable disease course in macular dystrophy. 5. p.Cys1010Tyr (c.3029G>A) - Another common missense variant affecting a conserved cysteine, leading to severe retinal dystrophy.
Clinical significance: Mutations in the CRB1 gene manifest clinically as a broad spectrum of autosomal recessive inherited retinal dystrophies (IRDs). The most prevalent and severe phenotype is Leber congenital amaurosis (LCA) or early-onset severe retinal dystrophy (EOSRD), which accounts for a significant portion of CRB1 cases. Patients with LCA/EOSRD typically present within the first few months or years of life with severe visual impairment, nystagmus, and an undetectable or severely reduced electroretinogram (ERG). Another common manifestation is retinitis pigmentosa (RP), often presenting as juvenile-onset RP with night blindness, progressive peripheral visual field loss, and reduced visual acuity. Distinctive clinical features of CRB1-associated retinopathies include a thickened, unlaminated retina on optical coherence tomography (OCT), preserved para-arteriolar retinal pigment epithelium (PPRPE), nummular pigmentation, and in some cases, Coats-like exudative vasculopathy. Less commonly, CRB1 mutations can cause macular dystrophy (MD) or cone-rod dystrophy (CORD), which typically present in early adulthood with central vision loss.
Inheritance: Autosomal Recessive
Chromosomal location: 1q31.3
Genotype-phenotype correlations: While CRB1 mutations cause a wide spectrum of retinopathies, establishing clear genotype-phenotype correlations has been challenging due to the clinical variability even among individuals with the same variants. However, some patterns have emerged. Severe phenotypes like Leber congenital amaurosis (LCA) and early-onset severe retinal dystrophy (EOSRD) are significantly associated with null variants, such as frameshift changes, nonsense mutations, and aberrant splicing, which lead to a complete loss of functional protein. Conversely, milder phenotypes like macular dystrophy (MD) have been linked to specific variants, such as the in-frame deletion c.498_506del (p.Ile167_Gly169del), which appears exclusively in MD cohorts. Additionally, missense mutations affecting specific domains, such as the transmembrane or intracellular domains, or those disrupting critical disulfide bonds, tend to correlate with increased disease severity and earlier onset.
Research and therapeutic approaches: Currently, there are no approved therapies specifically for CRB1-associated retinal dystrophies. Management is primarily supportive, focusing on correcting refractive errors, providing low-vision aids, and monitoring for complications such as cystoid macular edema (CME) or Coats-like exudative vasculopathy, which may require medical or surgical intervention. However, the disease is a major target for therapeutic research, particularly in the realm of gene therapy. Gene augmentation therapy is the leading investigational approach, aiming to deliver a functional copy of the CRB1 gene to the retina. A significant challenge is the large size of the CRB1 coding sequence, which exceeds the packaging capacity of standard adeno-associated virus (AAV) vectors. To overcome this, researchers are exploring strategies such as using dual AAV vectors, engineered minimal promoters, or delivering the smaller, related CRB2 gene to compensate for the loss of CRB1 function. Preclinical studies in mouse models have shown promising results, restoring retinal structure and function. While clinical trials for CRB1-specific gene therapies are still in the developmental or early phases, the success of Luxturna (voretigene neparvovec) for RPE65-related disease provides a strong proof-of-concept for this approach in inherited retinal diseases.
Diagnostic testing: Mutations in the CRB1 gene are typically detected through molecular genetic testing, which is essential for confirming the diagnosis and guiding management. Next-generation sequencing (NGS) approaches are the standard of care, including targeted retinal gene panels, whole exome sequencing (WES), or whole genome sequencing (WGS). These tests can identify the biallelic pathogenic variants responsible for the disease. Genetic counseling is a critical component of the diagnostic process. Since CRB1-associated retinopathies follow an autosomal recessive inheritance pattern, parents of an affected individual are obligate carriers (heterozygotes) and typically asymptomatic, though some studies suggest they may have subtle regional retinal dysfunction. Each sibling of an affected individual has a 25% chance of inheriting the condition, a 50% chance of being an asymptomatic carrier, and a 25% chance of being unaffected and not a carrier. Counseling helps families understand these risks, the natural history of the disease, and options for family planning.
Animal models: The primary animal models used to study CRB1-associated retinal dystrophies are mouse models (such as the Crb1 knockout mouse) and zebrafish. In mice, the loss of Crb1 function leads to retinal disorganization, abnormal lamination, and progressive retinal degeneration, mimicking aspects of the human disease. However, a prominent difference is that the human disease often presents with early and severe loss of retinal function, whereas the mouse model typically shows near-normal function initially with later degeneration. Zebrafish models have also been instrumental in understanding CRB1 biology. Interestingly, zebrafish Crb1 localizes uniquely to the cell membranes surrounding the axonemes of cone outer segments, differing from its localization in mammals. Studies in zebrafish have revealed that Crb1 promotes rod survival under strong light irradiation and delays chromatin condensation in cones caused by UV light, highlighting its role in photoreceptor maintenance and light responsiveness.
Population genetics: CRB1-associated retinal dystrophies are among the more common causes of inherited retinal diseases, accounting for approximately 10% of Leber congenital amaurosis (LCA) cases and up to 6.5% of autosomal recessive retinitis pigmentosa (RP) cases worldwide. The carrier frequency for CRB1 mutations varies by population but is generally estimated to be around 1 in 100 to 1 in 200 in the general population. Certain variants exhibit founder effects in specific populations; for instance, the c.2843G>A variant is particularly prevalent in some European cohorts. The overall prevalence of CRB1-related disease is estimated to affect roughly 1 in 80,000 individuals globally.
Selected references: 1. Daich Varela M, et al. CRB1-Associated Retinal Dystrophies: Genetics, Clinical Characteristics, and Natural History. Am J Ophthalmol, 2023. PMID: 36099972 2. den Hollander AI, et al. Mutations in a human homologue of Drosophila crumbs cause retinitis pigmentosa (RP12). Nat Genet, 1999. PMID: 10508510 3. Bujakowska K, et al. CRB1 mutations in inherited retinal dystrophies. Hum Mutat, 2012. PMID: 22334356 4. Talib M, et al. CRB1-Associated Retinal Dystrophies: A Prospective Natural History Study. Am J Ophthalmol, 2022. PMID: 34740398 5. Guo C, et al. Zebrafish Crb1, Localizing Uniquely to the Cell Membranes Surrounding the Cone Axonemes, Is Required for Cone Responsiveness to Light and Photoreceptor Maintenance. J Neurosci, 2020. PMID: 32769201 6. Richard M, et al. Towards understanding CRUMBS function in retinal dystrophies. Hum Mol Genet, 2006. PMID: 16987884 7. Gosens I, et al. Composition and function of the Crumbs protein complex in the mammalian retina. Exp Eye Res, 2008. PMID: 18384773