Vision Simulations










Retinitis Pigmentosa (RP)
Tunnel Vision — Peripheral Field Loss
Rod photoreceptors (peripheral retina → inward)
Autosomal dominant, autosomal recessive, or X-linked
RHO, USH2A, RPGR, RP1, PRPF31, and 60+ others
Retinitis Pigmentosa is the most common inherited retinal dystrophy, affecting approximately 1.5 million people worldwide. It primarily destroys rod photoreceptors, which are concentrated in the peripheral retina and responsible for night vision and side vision.
Early (Teens–20s)
Night blindness (nyctalopia) is typically the first symptom. Patients notice difficulty seeing in dim restaurants, movie theaters, or when driving at dusk. The peripheral visual field begins to constrict, but this is often unnoticed initially.
Moderate (20s–40s)
Progressive peripheral field loss creates 'tunnel vision.' Patients may bump into doorframes, trip over objects on the ground, or fail to notice people approaching from the side. The visual field may be reduced to 20-30 degrees (normal is ~180 degrees).
Advanced (40s+)
The visual field narrows to less than 10 degrees — like looking through a narrow tube or straw. Central vision may remain relatively preserved for years, allowing reading, but mobility becomes severely impaired. Some patients eventually lose central vision as well.
On fundoscopy, classic findings include bone-spicule pigmentation in the mid-periphery, attenuated retinal arterioles, and waxy pallor of the optic disc. ERG shows severely reduced or extinguished rod responses with relatively preserved cone responses in early stages. OCT reveals progressive outer retinal thinning from the periphery inward, with an ellipsoid zone (EZ) line that shortens over time.
Patients often describe feeling 'trapped in a spotlight' — they can see what's directly ahead but are completely blind to everything around them. This makes navigation in unfamiliar environments extremely challenging and dangerous. Patients cannot drive, have difficulty in crowds, and may appear clumsy or inattentive to others who don't understand their condition.
Stargardt Disease
Central Scotoma — Macular Vision Loss
Cone photoreceptors and RPE (macula/fovea)
Autosomal recessive (most common) or autosomal dominant
ABCA4 (95% of cases), ELOVL4, PROM1
Stargardt Disease is the most common inherited macular dystrophy, typically presenting in childhood or young adulthood. It is caused by mutations in the ABCA4 gene, which leads to toxic accumulation of lipofuscin (a fluorescent waste product) in the retinal pigment epithelium beneath the macula. This progressively destroys the cone photoreceptors responsible for central, detailed vision.
Early (Childhood–Teens)
Difficulty reading small print or seeing fine details. Colors may appear slightly less vivid. Visual acuity begins to decline (20/40 to 20/80). A small central blind spot may be noticed when trying to look directly at something.
Moderate (Teens–20s)
The central scotoma (blind spot) enlarges. Patients cannot see faces clearly, struggle to read even large print, and have difficulty recognizing people. Visual acuity typically drops to 20/200 (legal blindness). Patients learn to use eccentric viewing — looking slightly to the side of what they want to see.
Advanced (20s+)
Large central scotoma obscures most detailed vision. Visual acuity may be 20/400 or worse. However, peripheral vision remains intact, allowing independent mobility. Patients can navigate, walk, and detect motion but cannot read, drive, or recognize faces without assistive technology.
Fundus examination reveals yellow-white flecks (lipofuscin deposits) scattered around the macula, often with central macular atrophy appearing as a 'beaten bronze' lesion. Fundus autofluorescence (FAF) shows a characteristic 'dark choroid' on fluorescein angiography due to lipofuscin blocking background fluorescence. OCT shows progressive loss of the ellipsoid zone centrally with preservation peripherally.
Patients describe a 'hole' in the center of their vision — wherever they look directly, they cannot see. Reading becomes impossible without magnification. They cannot recognize faces, read signs, or see details on screens. However, they can walk independently, see obstacles, and navigate because their peripheral vision is preserved. This creates a paradox where patients 'look normal' but cannot perform visual tasks others take for granted.
Choroideremia
RPE, photoreceptors, and choroid (all three layers)
X-linked recessive (primarily affects males)
Choroideremia is an X-linked retinal dystrophy that progressively destroys the choroid, retinal pigment epithelium (RPE), and photoreceptors. Unlike RP which creates a smooth ring of peripheral loss, choroideremia produces a distinctive patchy, moth-eaten pattern of vision loss as scattered areas of the retina degenerate at different rates.
Early (Childhood)
Night blindness is typically the first symptom, often noticed in early childhood. Boys may be reluctant to play outside at dusk or in poorly lit areas. Initial visual field testing may show scattered small scotomas in the mid-periphery.
Moderate (20s–30s)
Multiple blind spots appear and grow throughout the visual field in an irregular pattern. Unlike RP's concentric constriction, choroideremia creates a 'Swiss cheese' effect with islands of preserved vision between areas of complete blindness. Night blindness worsens significantly.
Advanced (40s–60s)
The patches of vision loss merge, leaving only a small central island of preserved vision. This central island can persist for many years (sometimes into the 60s or 70s), providing useful reading vision. Eventually, even this central island is lost, resulting in complete blindness.
Fundoscopy reveals progressive, scalloped areas of chorioretinal atrophy where the underlying white sclera becomes visible due to complete loss of the choroid, RPE, and retina. The pattern is distinctly different from RP — atrophic areas have sharp borders and a characteristic 'scalloped' edge. FAF shows sharply demarcated areas of absent autofluorescence surrounded by normal tissue. Female carriers typically show a mosaic pattern of RPE changes on FAF but rarely have significant vision loss.
The irregular pattern of vision loss is particularly disorienting. Patients describe 'holes' appearing randomly in their visual field — they might see a person's head and feet but not their torso, or see parts of a sign but not others. This unpredictable pattern makes it difficult for others to understand what the patient can and cannot see. Navigation requires constant scanning to piece together a complete picture of the environment.
Cone Dystrophy
Color Loss, Glare & Central Blur
Cone photoreceptors (all three types: S, M, L)
CNGA3, CNGB3, GNAT2, PDE6C, PDE6H, and others
Cone Dystrophies selectively destroy the cone photoreceptors while initially sparing rods. Since cones are responsible for color vision, central acuity, and function in bright light, patients experience a distinctive combination of color blindness, central vision loss, and severe light sensitivity (photophobia) — essentially the opposite pattern of RP.
Early
Difficulty distinguishing colors, particularly reds and greens. Increased sensitivity to bright light — patients may squint or avoid outdoor activities on sunny days. Mild reduction in central visual acuity (20/40 to 20/60). Colors appear 'washed out' or less vivid than they used to be.
Moderate
Significant color vision loss — the world appears increasingly gray and desaturated. Central vision becomes blurry, making reading difficult. Severe photophobia — bright environments cause pain and glare that overwhelms remaining vision. Patients often wear very dark sunglasses even indoors.
Advanced
Near-complete color blindness (acquired achromatopsia). Central acuity may drop to 20/200 or worse. Paradoxically, patients may see BETTER in dim light than bright light because their preserved rods function well in scotopic conditions. Peripheral vision remains intact.
ERG shows reduced or absent photopic (cone) responses with preserved scotopic (rod) responses — the opposite of RP. Fundoscopy may show a 'bull's eye' maculopathy pattern with central RPE atrophy surrounded by a ring of hyperpigmentation. Color vision testing (Ishihara, Farnsworth D-15) reveals progressive dyschromatopsia. OCT shows selective loss of the foveal ellipsoid zone with preserved peripheral outer retinal structure.
Patients describe the world as 'bleached out' and painfully bright. They cannot tolerate sunlight, fluorescent lighting, or even moderately bright indoor environments without extreme discomfort. Reading becomes difficult due to central blur. They cannot distinguish traffic lights by color (must use position), cannot match clothing colors, and struggle with any task requiring color discrimination. Ironically, they function best at night or in very dim environments — the opposite of RP patients.
Achromatopsia (Rod Monochromacy)
Complete Color Blindness & Light Sensitivity
All cone photoreceptors (non-functional from birth)
CNGA3, CNGB3, GNAT2, PDE6C, PDE6H, ATF6
Achromatopsia is a congenital (present from birth) condition where all three types of cone photoreceptors are absent or non-functional. Patients rely entirely on their rod photoreceptors for all vision. Since rods cannot detect color, cannot function in bright light, and provide low-resolution vision, patients experience complete color blindness, extreme light sensitivity, and reduced visual acuity from birth. Unlike progressive cone dystrophies, achromatopsia is typically stable and non-progressive.
From Birth (Stable)
Complete absence of color vision — the world is seen entirely in shades of gray. Severe photophobia — any bright light is painful and overwhelming because rods are saturated by normal daylight levels. Visual acuity is typically 20/200 (legal blindness) because rods have much lower spatial resolution than cones. Nystagmus (involuntary eye movements) is present from infancy.
Childhood Adaptation
Children learn to cope with their condition through behavioral adaptations: wearing very dark red-tinted glasses outdoors, preferring dim indoor environments, sitting close to screens, and using large print. They may struggle in bright classrooms and outdoor activities.
Adult Life (Stable)
Vision typically remains stable throughout life (non-progressive). Patients develop sophisticated coping strategies. They can navigate independently using brightness and contrast cues rather than color. Many achieve normal educational and professional outcomes with appropriate accommodations (screen magnification, lighting control, tinted lenses).
ERG shows completely absent photopic responses with normal scotopic responses. Fundoscopy is typically normal (no structural degeneration visible). OCT may show subtle foveal hypoplasia (underdevelopment of the foveal pit) or disruption of the foveal ellipsoid zone. Color vision testing shows complete failure on all plates/arrangements. The condition is stationary — unlike cone dystrophies, there is no progressive deterioration of retinal structure.
Patients live in a world without color — they have never seen red, blue, green, or any chromatic hue. Bright environments that others find pleasant are painfully overwhelming. A sunny day at the beach is an agonizing experience without extremely dark specialized filters. However, patients often develop exceptional night vision and contrast sensitivity because their rod system is highly developed. Many describe seeing better than sighted companions in very dim conditions.
Macular Dystrophy (Best Disease)
Central Distortion & Metamorphopsia
RPE and macular cone photoreceptors
Autosomal dominant (Best Disease) or various
~1 in 10,000 (all macular dystrophies combined)
BEST1 (Best Disease), PRPH2, IMPG1, IMPG2
Macular dystrophies encompass a group of conditions that primarily affect the macula — the central area of the retina responsible for detailed vision. Best Disease (Best Vitelliform Macular Dystrophy) is the most well-known, caused by mutations in the BEST1 gene that disrupt RPE function. Unlike Stargardt's complete central scotoma, macular dystrophies often cause distortion (metamorphopsia) where straight lines appear wavy or bent, along with blurred central vision.
Often discovered incidentally on eye exam — the classic 'egg yolk' (vitelliform) lesion is visible on fundoscopy before symptoms appear. Mild blurring of central vision may be noticed. Straight lines may appear slightly wavy when looking at grids or text.
Moderate (Variable)
Metamorphopsia becomes more pronounced — door frames, text lines, and faces appear distorted and wavy. Central vision becomes blurry and foggy. Reading becomes difficult as letters appear to swim or shift. Visual acuity drops to 20/60–20/100. The Amsler grid test shows obvious distortion.
Advanced (Variable)
The vitelliform lesion ruptures ('scrambled egg' stage) and atrophy develops. Central vision may drop to 20/200 or worse. Significant central scotoma may develop similar to Stargardt. However, progression is highly variable — some patients maintain useful vision for decades while others deteriorate more rapidly.
Best Disease shows a characteristic progression on fundoscopy: vitelliform (egg yolk) stage → pseudohypopyon (layering) → vitelliruptive (scrambled egg) → atrophic stage. EOG (electro-oculogram) shows a reduced Arden ratio (light peak/dark trough < 1.5), which is pathognomonic even in carriers. OCT reveals subretinal hyperreflective material corresponding to the vitelliform lesion, with progressive outer retinal disruption in later stages.
The distortion (metamorphopsia) is particularly frustrating for patients. Straight lines appear wavy, faces look distorted, and text seems to swim on the page. Unlike a simple blur that magnification can fix, distortion cannot be corrected with glasses or magnifiers. Patients may see a person's face as if reflected in a funhouse mirror. Reading requires significant effort as letters shift and warp. However, peripheral vision remains excellent, allowing normal mobility.
Usher Syndrome
Rod photoreceptors (retina) + hair cells (inner ear)
~3–6 per 100,000 (leading cause of deaf-blindness)
MYO7A (Type 1), USH2A (Type 2), CLRN1 (Type 3), CDH23, PCDH15
Usher Syndrome is the most common condition causing combined deafness and blindness. It accounts for approximately 50% of all hereditary deaf-blindness. The syndrome affects both the photoreceptors in the retina (causing RP-like progressive vision loss) and the hair cells in the inner ear (causing sensorineural hearing loss). Three clinical types exist with varying severity and onset of hearing and vision loss.
Type 1 (Most Severe)
Profound deafness from birth, absent vestibular function (balance problems, delayed walking), and RP onset in the first decade. Children are born profoundly deaf and develop progressive tunnel vision starting around age 10. By their 20s-30s, significant visual field constriction occurs while they are already relying heavily on sign language — which becomes increasingly difficult to see.
Type 2 (Most Common)
Moderate-to-severe hearing loss from birth (can often use hearing aids), normal balance, and RP onset in teens/young adulthood. Night blindness typically begins in the late teens, with progressive peripheral field loss through the 20s-40s. Hearing remains stable but vision progressively narrows.
Type 3 (Progressive)
Normal or near-normal hearing at birth that progressively worsens, variable vestibular function, and RP onset in the second decade. Both hearing and vision deteriorate simultaneously over decades, creating a uniquely challenging dual sensory loss that worsens over time.
Retinal findings are identical to non-syndromic RP: bone-spicule pigmentation, attenuated vessels, and optic disc pallor. ERG shows reduced rod responses progressing to extinguished responses. Audiometry reveals the characteristic hearing loss pattern for each type. Genetic testing is essential for type classification and prognosis. USH2A mutations are the most common cause overall.
Usher Syndrome creates a devastating dual sensory loss. As vision narrows, patients who rely on sign language find it increasingly difficult to see their conversation partners' hands. Those who use hearing aids find that as their visual field constricts, they can no longer lip-read to supplement their hearing. Communication becomes extremely challenging — patients may need tactile sign language (signing into someone's hands) in advanced stages. The combination of tunnel vision and hearing loss makes navigation in noisy, crowded environments particularly dangerous and isolating.
Leber Congenital Amaurosis (LCA)
Photoreceptors and/or RPE (generalized, from birth)
Autosomal recessive (most) or autosomal dominant (rare)
RPE65, CEP290, GUCY2D, CRB1, AIPL1, RPGRIP1, and 20+ others
Leber Congenital Amaurosis is one of the most severe inherited retinal dystrophies, causing profound vision loss from birth or the first few months of life. It accounts for approximately 5% of all inherited retinal dystrophies but is responsible for 20% of childhood blindness in special education settings. LCA is historically significant as the target of Luxturna (voretigene neparvovec), the first FDA-approved gene therapy for an inherited disease.
Infancy (0–12 months)
Parents notice the infant does not fixate on faces or track objects. Nystagmus (rhythmic eye movements) develops. The oculodigital sign (Franceschetti sign) is characteristic — infants press, poke, or rub their eyes to generate phosphenes (light flashes) for visual stimulation. Pupils may react sluggishly to light. ERG is extinguished or severely reduced.
Childhood
Visual acuity ranges from light perception only to approximately 20/400 depending on the genetic subtype. Some children can detect large objects and navigate familiar environments using residual vision. Others have no useful form vision and rely entirely on non-visual senses. Hyperopia (farsightedness) and keratoconus may develop.
Variable Progression
Course depends heavily on the causative gene. RPE65-LCA may be relatively stable (and treatable with Luxturna). CEP290-LCA tends to be severe from birth. CRB1-LCA may show some progression. GUCY2D-LCA often has better preserved retinal structure despite poor function, making it a promising gene therapy target.
Fundoscopy findings vary by genotype: may be normal in infancy (RPE65, GUCY2D), show salt-and-pepper pigmentary changes, macular coloboma-like lesions (CRB1), or nummular pigment clumps. ERG is characteristically extinguished or severely attenuated in both scotopic and photopic conditions from infancy — this is the key diagnostic finding. OCT shows variable outer retinal preservation depending on genotype, which is critical for gene therapy eligibility assessment.
Children with LCA grow up with severe visual impairment from birth. Many are legally blind or have only light perception. They learn to navigate the world primarily through touch, hearing, and spatial memory. Despite this, with early intervention, appropriate education, and assistive technology, many individuals with LCA lead independent, fulfilling lives. The approval of Luxturna for RPE65-LCA has provided hope — treated patients can gain functional vision sufficient for independent navigation, though not normal acuity.
Rod-Cone Dystrophy & Night Blindness
Night Vision Loss Progressing to Tunnel Vision
Rod photoreceptors first, then cones
Variable (AD, AR, or X-linked depending on gene)
Included within RP prevalence (~1 in 4,000)
Same as RP: RHO, USH2A, RPGR, RP1, etc.
Rod-Cone Dystrophy is the clinical term for the pattern of photoreceptor degeneration seen in Retinitis Pigmentosa and related conditions. The name emphasizes that rods are affected first and most severely, with cone involvement occurring later. The earliest and most impactful symptom is night blindness (nyctalopia) — the complete inability to see in dim lighting conditions that others navigate easily.
Night Blindness (First Symptom)
The earliest symptom is difficulty seeing in dim light. Patients cannot see in restaurants, movie theaters, or outdoors at dusk. While others can navigate by moonlight or streetlamps, rod-cone dystrophy patients are effectively blind in these conditions. This occurs because rod photoreceptors — which provide all dim-light vision — are the first to die.
Dark Adaptation Failure
Normal eyes take 20-30 minutes to fully adapt to darkness (dark adaptation). Rod-cone dystrophy patients either cannot dark-adapt at all or reach a much higher threshold — meaning even after waiting in the dark, they still cannot see what others can. Transitioning from bright to dim environments (e.g., entering a building from sunlight) causes prolonged functional blindness.
Progression to Daytime Symptoms
Over years to decades, the disease progresses from pure night blindness to daytime peripheral field loss (tunnel vision) as rod death extends into the mid-periphery and eventually cones begin to die as well. The pattern follows the classic RP trajectory: night blindness → peripheral constriction → tunnel vision → potential central vision loss.
Dark adaptometry testing quantifies the rod threshold elevation — patients may have thresholds elevated by 3-5 log units above normal, meaning they need 1,000 to 100,000 times more light than normal to see. ERG shows reduced or absent scotopic (rod) responses before photopic (cone) responses are affected. Goldmann visual field testing documents the progressive peripheral constriction over time.
Night blindness profoundly affects quality of life in ways others rarely appreciate. Patients cannot: drive after sunset, navigate parking lots at night, find their seat in a dark theater, see steps or curbs in dim lighting, or participate in evening social activities without assistance. Many patients describe feeling 'imprisoned by darkness' — their world shrinks dramatically after sunset. This is often the symptom that first brings patients to seek diagnosis, sometimes decades before significant daytime vision loss occurs.
Vision Loss Simulations
See through the eyes of IRD patients. Interactive simulations showing how retinitis pigmentosa, Stargardt, and other IRDs affect vision.
Understanding Vision Loss
See the world through the eyes of someone living with an inherited retinal disease. These medically accurate simulations show how different IRDs affect vision — from tunnel vision to central blind spots, color loss to complete darkness — along with animated progressions showing how these conditions worsen over time.
Important Note: These simulations are approximations designed to help sighted individuals understand the visual experience of IRD patients. Actual vision loss varies significantly between individuals, even with the same diagnosis.
Normal Vision — Reference Baseline
The image below represents normal, healthy vision with full color perception, sharp focus from center to periphery, and a complete ~180-degree visual field. All subsequent simulations use a similar scene to demonstrate how each condition alters this baseline.
Normal vision: Full color, sharp focus, complete peripheral field (~180°), good contrast in all lighting conditions
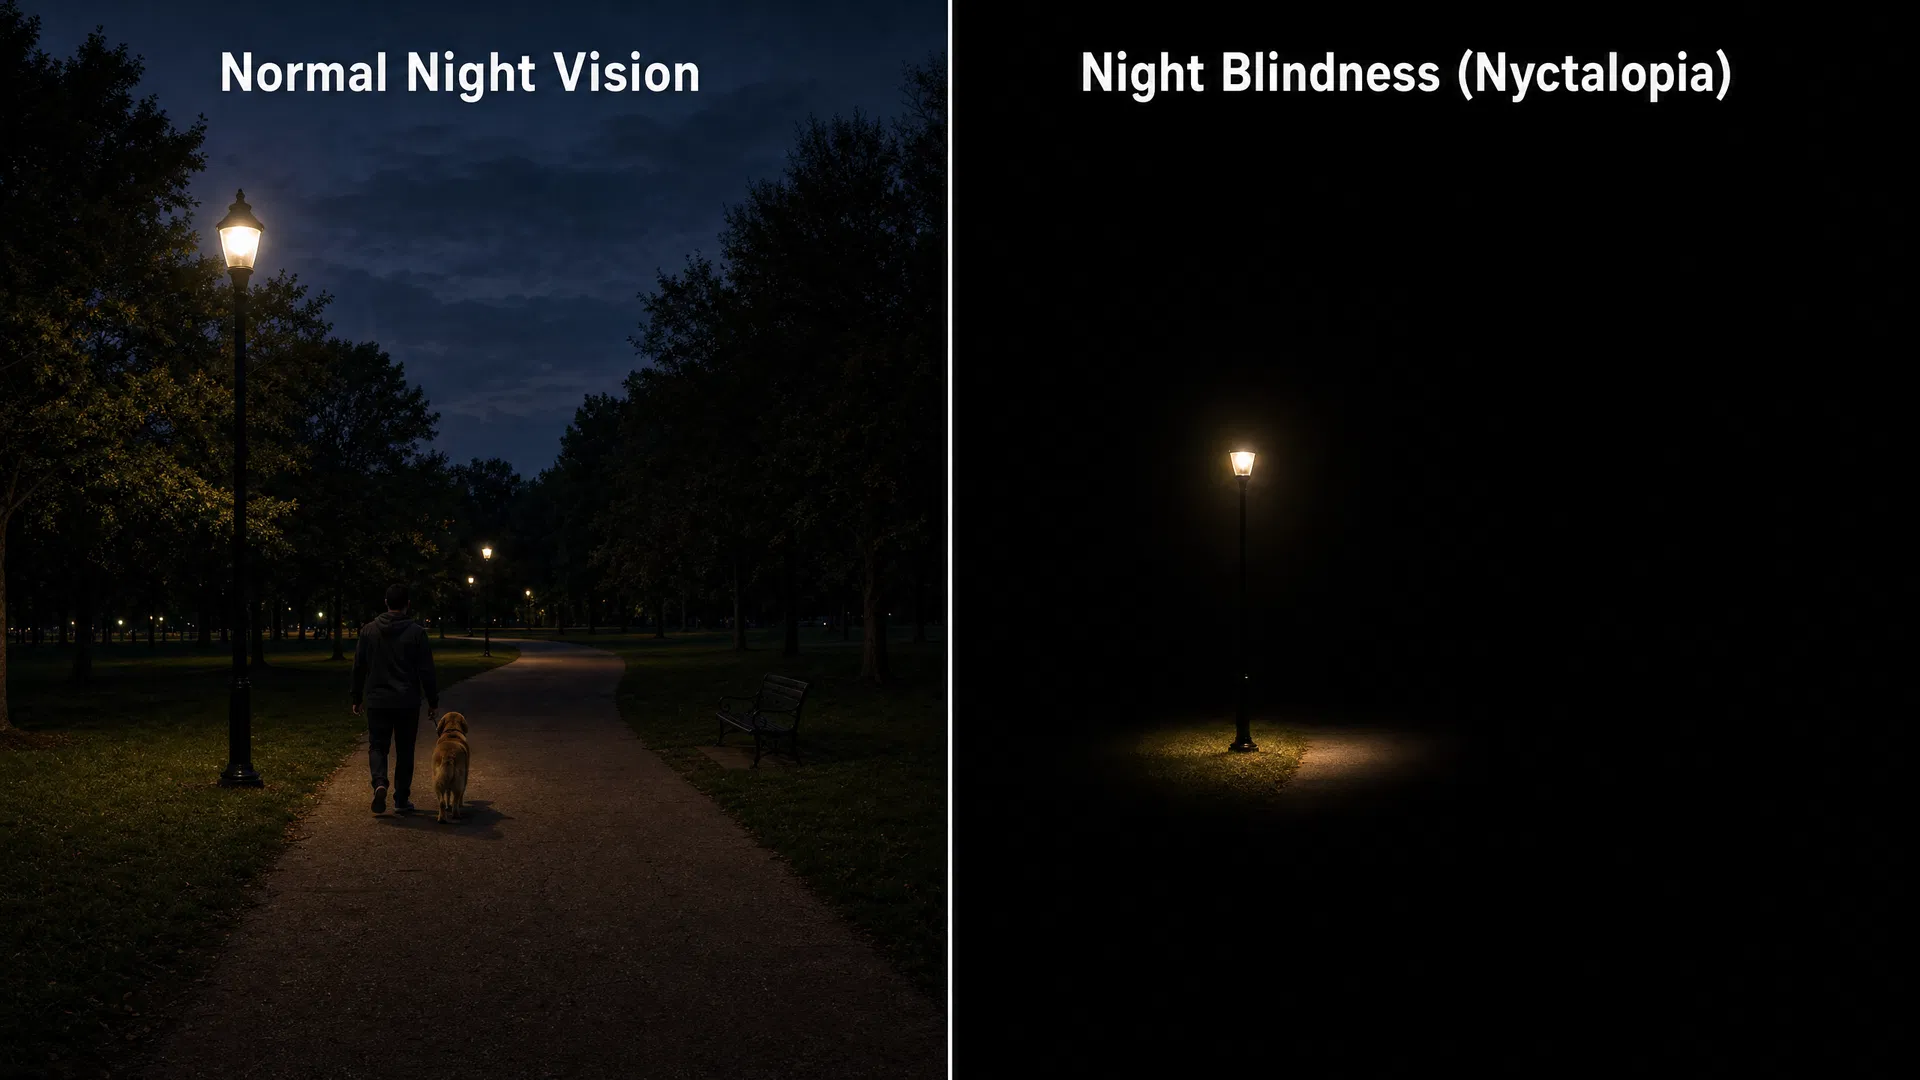
Night Blindness (Nyctalopia) — A Common First Symptom
Night blindness is often the earliest symptom of rod-affecting IRDs including Retinitis Pigmentosa, Choroideremia, Usher Syndrome, and Congenital Stationary Night Blindness. The comparison below shows the dramatic difference between normal night vision and the experience of someone with nyctalopia.
Left: Normal scotopic (night) vision — objects visible in dim light. Right: Night blindness — only areas directly illuminated are visible.
Interactive Comparison — Drag to Compare
Drag the slider to compare normal vision with
Full Simulation View
Simulated view through the eyes of a patient with
Disease Progression Animation
This animation shows how vision changes over time as the disease progresses from early to advanced stages. In reality, this progression occurs over years to decades.
Animated progression: Normal vision → Advanced (actual progression occurs over years)
Symptoms & Progression Timeline
Clinical & Diagnostic Notes
Impact on Daily Life
Comparison: How Different IRDs Affect Vision
Condition
Pattern of Loss
Color Affected?
Night Vision
Central Vision
Peripheral Vision
Retinitis Pigmentosa
Peripheral → Central (ring)
Late stages only
Severely impaired
Preserved (early/mid)
Lost progressively
Central scotoma
Mildly reduced
Normal
Lost (scotoma)
Preserved
Patchy / moth-eaten
In affected areas
Preserved until late
Patchy loss
Central blur + color loss
Severely affected
Normal or better
Blurred
Achromatopsia
Generalized (stable)
Complete color blindness
Excellent (rod-only)
Reduced acuity (20/200)
Macular Dystrophy
Central distortion
Centrally affected
Distorted (wavy)
Peripheral (+ hearing loss)
LCA
Generalized (from birth)
Learn More About These Conditions
Explore our comprehensive database of inherited retinal diseases to learn about specific conditions, associated genes, available treatments, and ongoing clinical trials.
Vision & Eye Anatomy
Learn how the eye works — from cornea to visual cortex — and understand what goes wrong in IRDs.
Newly Diagnosed Guide
Essential first steps and resources for those recently diagnosed with an IRD.
IRD Conditions Database
Explore detailed profiles of 53 inherited retinal diseases with genetics, symptoms, and treatments.