Why metabolic treatment matters in Alström syndrome
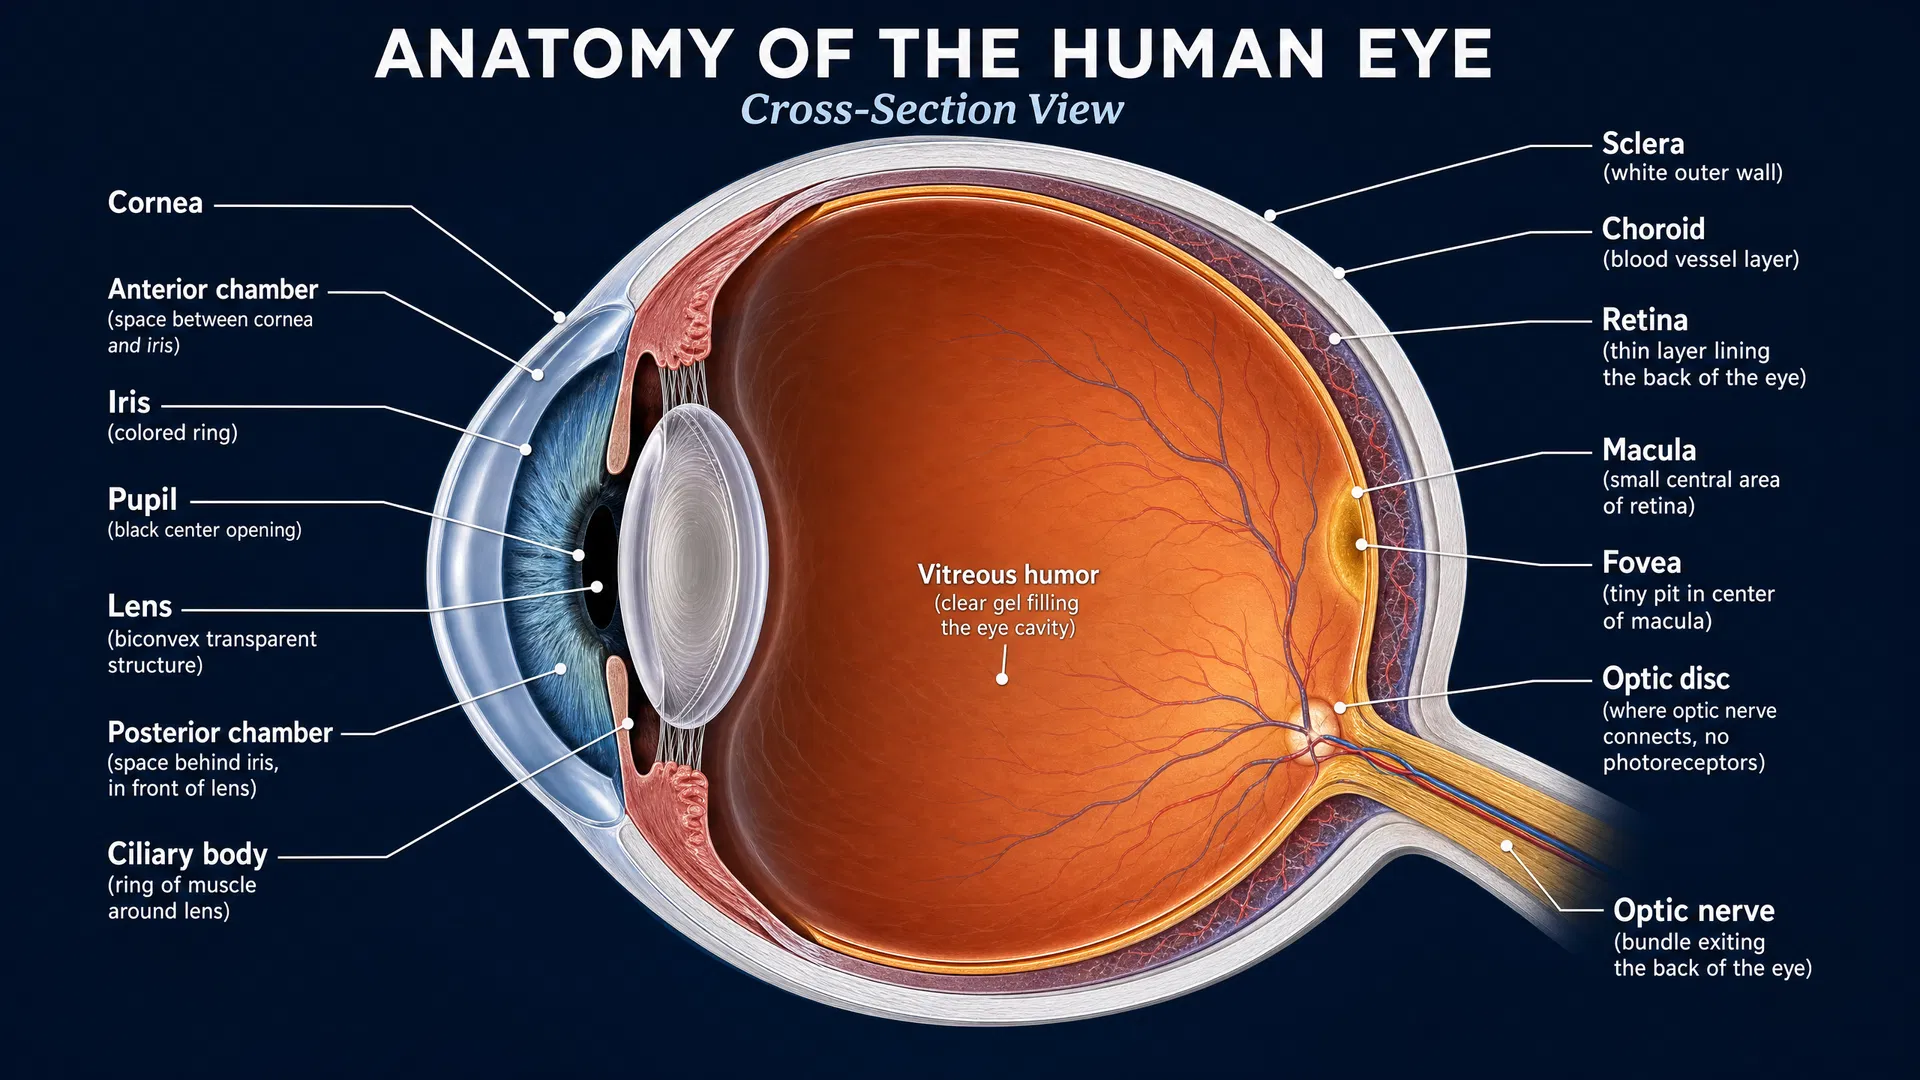
Alström syndrome is a rare inherited condition caused by changes in the ALMS1 gene. These changes disrupt the function of cellular cilia—tiny structures that help cells sense and respond to their environment—and can affect many organs over time. Families may be most familiar with the condition’s early and progressive vision loss from retinal degeneration, as well as hearing loss. However, metabolic complications can become equally important to health and quality of life.
People with Alström syndrome often develop obesity, severe insulin resistance, type 2 diabetes, fatty liver disease, abnormal blood lipids, kidney disease, and cardiomyopathy. Insulin resistance means the body does not respond effectively to insulin, requiring the pancreas to produce more of it to keep blood glucose under control. In Alström syndrome, this problem can be particularly severe and can progress rapidly during adolescence.
A 2026 follow-up case report in Frontiers in Endocrinology examines whether ertugliflozin, a sodium-glucose cotransporter-2 (SGLT2) inhibitor, could help address some of these metabolic challenges in two siblings with Alström syndrome.
How ertugliflozin works
Ertugliflozin is already approved for blood-glucose management in type 2 diabetes. It works through the kidneys: it reduces the reabsorption of glucose back into the bloodstream, allowing more glucose to leave the body in urine. This mechanism differs from treatments that primarily increase insulin production or improve the body’s response to insulin.
That distinction makes SGLT2 inhibitors of interest in Alström syndrome, where insulin resistance may be profound. The clinical management guidelines for Alström syndrome emphasize careful management of diabetes and associated metabolic disease. This report adds longitudinal observations on one potential treatment option within that wider care approach.
What the researchers studied
The researchers retrospectively reviewed clinical records from two siblings with Alström syndrome treated at their endocrinology department. Both received ertugliflozin and were followed for 11 months. The team assessed changes in blood-glucose control, insulin resistance, and lipid metabolism, while also monitoring safety.
Because the report involved two related individuals rather than a larger clinical trial, it provides a detailed view of treatment experience in this family but cannot establish how the medicine will perform across the broader Alström syndrome population.
Key findings: better glucose control and early insulin-sensitivity gains
Both siblings experienced improved glycemic control. Their HbA1c levels—a measure that reflects average blood-glucose levels over roughly the previous two to three months—fell significantly by month 2 of treatment. The report also documented reductions in fasting and post-meal glucose concentrations, findings that align with the glucose-lowering action expected from an SGLT2 inhibitor.
Measures of insulin resistance also improved early in treatment. In Patient 1, the homeostatic model assessment of insulin resistance, known as HOMA-IR, showed marked improvement. HOMA-IR is calculated from fasting glucose and insulin measurements and is commonly used as an estimate of how strongly the body is resisting insulin’s effects.
Patient 2 showed an early improvement in HOMA-IR as well, supported by dynamic glucose-tolerance testing. Later in follow-up, however, HOMA-IR rose again. The authors noted that this younger sibling was in puberty, a period when the severe and rapidly progressive insulin resistance associated with Alström syndrome may intensify. The report cannot separate the long-term effect of ertugliflozin from the underlying progression of diabetes and insulin resistance in this patient.
Effects on lipids and safety
The report also found favorable changes in lipid metabolism, including modest improvement in total cholesterol. The authors could not determine ertugliflozin’s individual effect on triglycerides in one sibling because that patient was also taking a fibrate, a medication used to lower triglyceride levels.
Importantly, no adverse events were reported during the 11-month treatment period, and ertugliflozin was generally well tolerated by both patients. This is encouraging, particularly because people with Alström syndrome may need coordinated treatment for several interacting metabolic, heart, liver, and kidney concerns.
What this could mean for treatment
This report suggests that ertugliflozin may contribute to improved glucose control in Alström syndrome and may offer early benefits for insulin sensitivity and blood lipids. For clinicians, it reinforces the value of individualized metabolic care that considers established diabetes treatments alongside the multisystem features of Alström syndrome.
The differing insulin-resistance patterns in the two siblings are also meaningful. They illustrate that treatment responses may vary with age, developmental stage, disease progression, and other medications. Puberty may be an especially important period for close metabolic monitoring.
Building the evidence base
Alström syndrome research faces a familiar challenge: the condition is rare, making large studies difficult to conduct. Yet carefully reported patient experiences can identify promising approaches and help shape future research. The next step is prospective, controlled clinical research involving more people with Alström syndrome, with longer follow-up and more detailed biological measures.
For now, this two-sibling report provides an early signal that SGLT2 inhibition deserves further study as part of the evolving treatment landscape for the metabolic complications of Alström syndrome.