Why this case matters
Bardet-Biedl syndrome (BBS) is an inherited condition that can affect many body systems. Its features may include retinal dystrophy, extra fingers or toes (postaxial polydactyly), kidney disease, obesity, differences in sexual development, and metabolic complications such as diabetes. However, not every person develops these features at the same age or in the same combination. This wide clinical variation can delay recognition and genetic diagnosis.
A 2026 case report in Experimental and Therapeutic Medicine describes a 31-year-old woman whose longstanding, poorly controlled type 2 diabetes was the main reason she came to medical attention. Her case illustrates an important message for people with BBS, families, and clinicians: diabetes and other metabolic concerns may be a prominent part of BBS and can sometimes overshadow the underlying genetic diagnosis.
A multisystem pattern behind diabetes
The patient had adult-onset type 2 diabetes with associated complications and difficulty achieving glycemic control. On further evaluation, she was also found to have several features classically associated with BBS:
- Class I obesity
- Retinal dystrophy
- Postaxial polydactyly
- Renal dysfunction
- Hypergonadotropic hypogonadism, a form of impaired gonadal function in which hormone signals from the brain are elevated
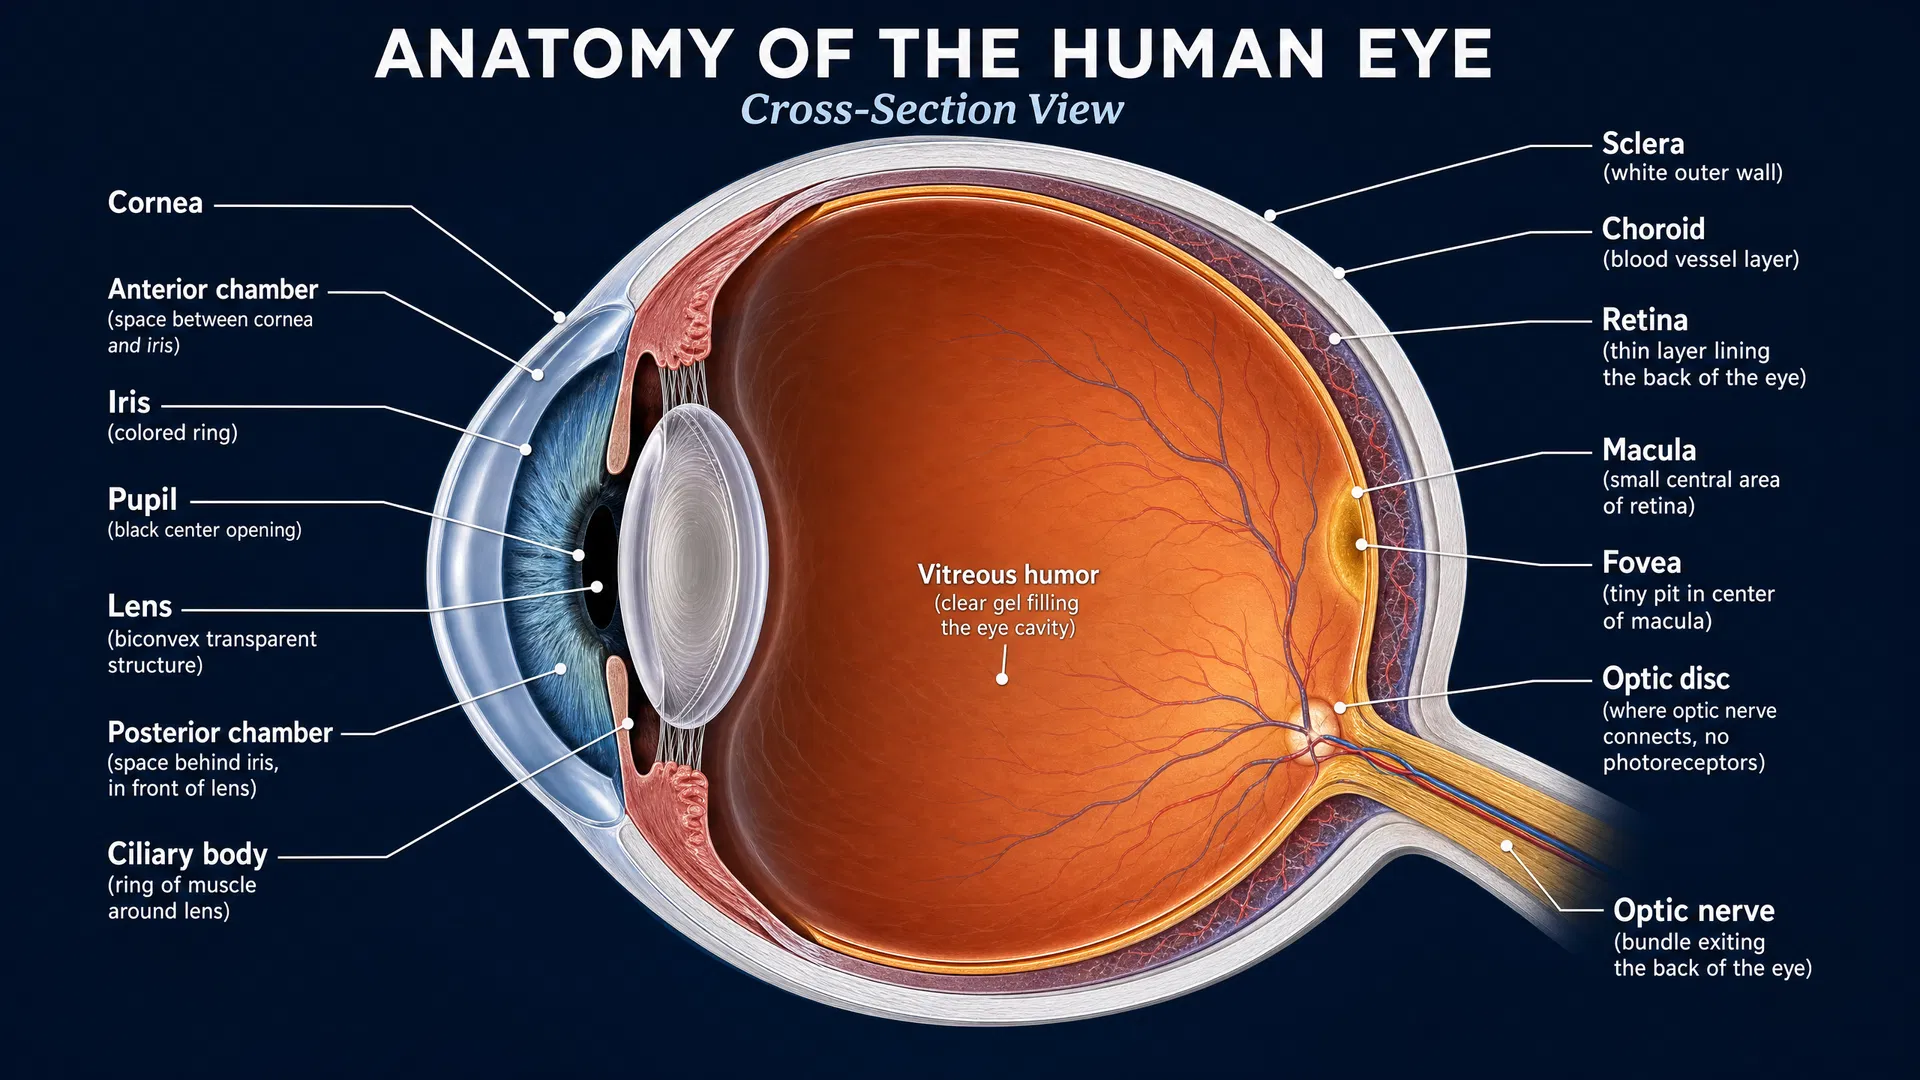
Any one of these findings may have multiple possible causes. Together, however, they formed a recognizable pattern pointing toward Bardet-Biedl syndrome. This is particularly significant because retinal dystrophy can lead to progressive vision impairment, while kidney and metabolic involvement may have major effects on long-term health.
The report emphasizes that BBS should be considered when early metabolic disease occurs alongside findings in other systems—especially vision changes, extra digits, kidney concerns, obesity, or reproductive-hormone differences. Recognizing this pattern may help connect what can otherwise appear to be unrelated health issues.
Genetic testing identified changes in BBS10
Whole-exome sequencing provided the definitive diagnosis. The patient had two different disease-causing variants in BBS10, one inherited on each copy of the gene—a pattern known as compound heterozygosity. One variant was a nonsense change, p.Arg256*, which introduces an early stop signal in the genetic instructions. The other was a missense variant, p.Gly180Glu, which changes one building block of the BBS10 protein.
BBS10 is among the genes associated with Bardet-Biedl syndrome. BBS is classified as a ciliopathy because the involved genes affect the function of cilia—small, antenna-like structures on cells that help coordinate signaling. Since cilia are important in many tissues, disruption of ciliary function can help explain why BBS affects the retina, kidneys, metabolism, and reproductive system.
For families, a molecular diagnosis can be valuable beyond simply naming a condition. It can clarify the cause of a person’s multisystem symptoms, guide coordination of care, and inform genetic counseling for relatives and future family planning.
Semaglutide and metabolic care in BBS
An especially notable aspect of this report was the patient’s improvement in glycemic control after treatment with semaglutide, a glucagon-like peptide-1 receptor agonist, often shortened to GLP-1 receptor agonist. These medicines are used to improve blood glucose management in type 2 diabetes and can also support weight management in some settings.
The authors suggest that the response may be relevant to BBS biology. GLP-1 receptors belong to a large group of cell-surface proteins called G-protein-coupled receptors, which relay signals into cells. Because BBS involves ciliary dysfunction and altered signaling, the observed response raises the possibility that GLP-1 receptor-directed treatment may remain useful even when cilia-related pathways are affected.
Importantly, this was one patient’s experience, not a clinical trial. It cannot establish that semaglutide will be effective for every person with BBS or define the best dose, duration, or treatment combination. Still, the report contributes longitudinal clinical evidence that targeted metabolic therapies may be a meaningful part of care for some people with BBS-associated diabetes.
Looking ahead
This case broadens understanding of how BBS10-related Bardet-Biedl syndrome may present in adulthood. It also reinforces the need to look beyond a single diagnosis—such as type 2 diabetes—when metabolic disease occurs with retinal, kidney, limb, or reproductive findings.
Future research will need to examine GLP-1 receptor agonists and other metabolic treatments in larger groups of people with BBS. Studies that pair detailed genetic findings with long-term clinical outcomes may help identify whether particular gene variants, symptoms, or signaling pathways influence treatment response. As genetic testing becomes more integrated into care, earlier diagnosis may also create more opportunities to monitor vision, kidney health, and metabolic complications before they become more severe.